









The FDA Wants to Pull Its Approval of a Drug. It’s Not So Easy.


In May 2021, the U.S. Food and Drug Administration released a lengthy briefing document on an experimental medication for a rare autoimmune form of vasculitis that often damages the kidneys and lungs. The agency was on the fence about whether to approve the treatment, and it wanted an independent advisory committee to weigh in. Among the questions at hand: Was the drug meaningfully better than existing therapies?
Participants in the study, which had been conducted by the California biotechnology company ChemoCentryx, did appear to have slightly higher rates of symptom remission after one year. But according to the FDA, it was hard to interpret the results because the study’s design had been less than optimal. Some advisory committee members expressed a similar view. The effect of the drug, said one, “is just not well verified by this study.”

At the same time, many patients, and some physicians, saw in the data a potentially helpful medication, one that might lessen patients’ reliance on steroids, which are highly effective but often cause severe side effects.
The advisory committee ultimately voted narrowly to recommend approval, and the FDA followed that advice, greenlighting the drug on Oct. 7, 2021. The drug, marketed as Tavneos, started making its way into clinics. A year after approval, ChemoCentryx was acquired by Amgen, one of the world’s largest pharmaceutical companies. The cost, even today, isn’t minor: $220,000 per year, according to Drugs.com. In fiscal year 2025, sales of Tavneos reached nearly half a billion dollars.
This financial windfall has unfolded despite a long-roiling investor lawsuit — one that incidentally uncovered what the FDA today believes is evidence that ChemoCentryx employees manipulated the data in the pivotal trial submitted to the agency. In April of this year, the FDA issued a letter proposing that Tavneos be withdrawn from the U.S. market, citing reports of serious, sometimes fatal, liver injury, and arguing that the drug now lacks “substantial evidence” that it works.
These revelations have triggered a dramatic cascade of events. This summer, the New England Journal of Medicine retracted a paper describing the clinical trial and Tavneos was taken off the market in the European Union. The United Kingdom has announced that it, too, will remove the product from the market. And on Oct. 29, a court hearing will proceed over Zoom to consider a proposed $69 million settlement for the lawsuit.
But the fate of Tavneos, at least in the United States, is far from sealed. Amgen has pushed back against its critics, insisting that — whatever the details of ChemoCentryx’s data handling — its drug works as advertised and should stay on the market. In July, the company submitted a 104-page document to the FDA stating that “the totality of the evidence supports the continued availability of TAVNEOS.”
The dispute is emblematic of the FDA’s longstanding struggle to regulate drugs of uncertain efficacy.
Some patients and academic experts also believe the drug is an important treatment option. “This appears to be an efficacious medication,” said Eric Roberts, an epidemiologist at the University of California, San Francisco, who co-authored an independent registry study of Tavneos.
The dispute is emblematic of the FDA’s longstanding struggle to regulate drugs of uncertain efficacy, said Reshma Ramachandran, a physician and co-director of the Yale Collaboration for Regulatory Rigor, Integrity, and Transparency. Absent more rigorous studies, either before or after a drug goes on the market, Ramachandran worries, “we’re just going to be living in uncertainty in terms of whether or not these drugs actually work.”
For American consumers, the saga of Tavneos also raises potent questions around the safeguards in place to ensure the integrity of drug approvals, particularly when a relatively small company conducts the pivotal trial and has so much riding on the success of a single drug.
Chloe Cusano was a 20-year-old college student when she was struck, this past December, with unbearable pain in her legs, as well as bouts of breathlessness from routine tasks like walking upstairs or bending down to retrieve her dog’s water dish. After going to the emergency room, she was hospitalized for more than two weeks, during which she was diagnosed with ANCA-associated vasculitis, or AAV, an umbrella term for a group of rare diseases in which the immune system mistakenly attacks its own blood vessels. When it was first identified, the condition was usually fatal.
Over the past four decades, scientists have developed drugs that allow many AAV patients to live a relatively normal lifespan. Because the disease can rapidly lead to organ failure, particularly of the kidneys and lungs, patients are immediately started on a high dose of steroids to rapidly tamp down inflammation. They also typically receive slower-acting medications that target the underlying disease process.
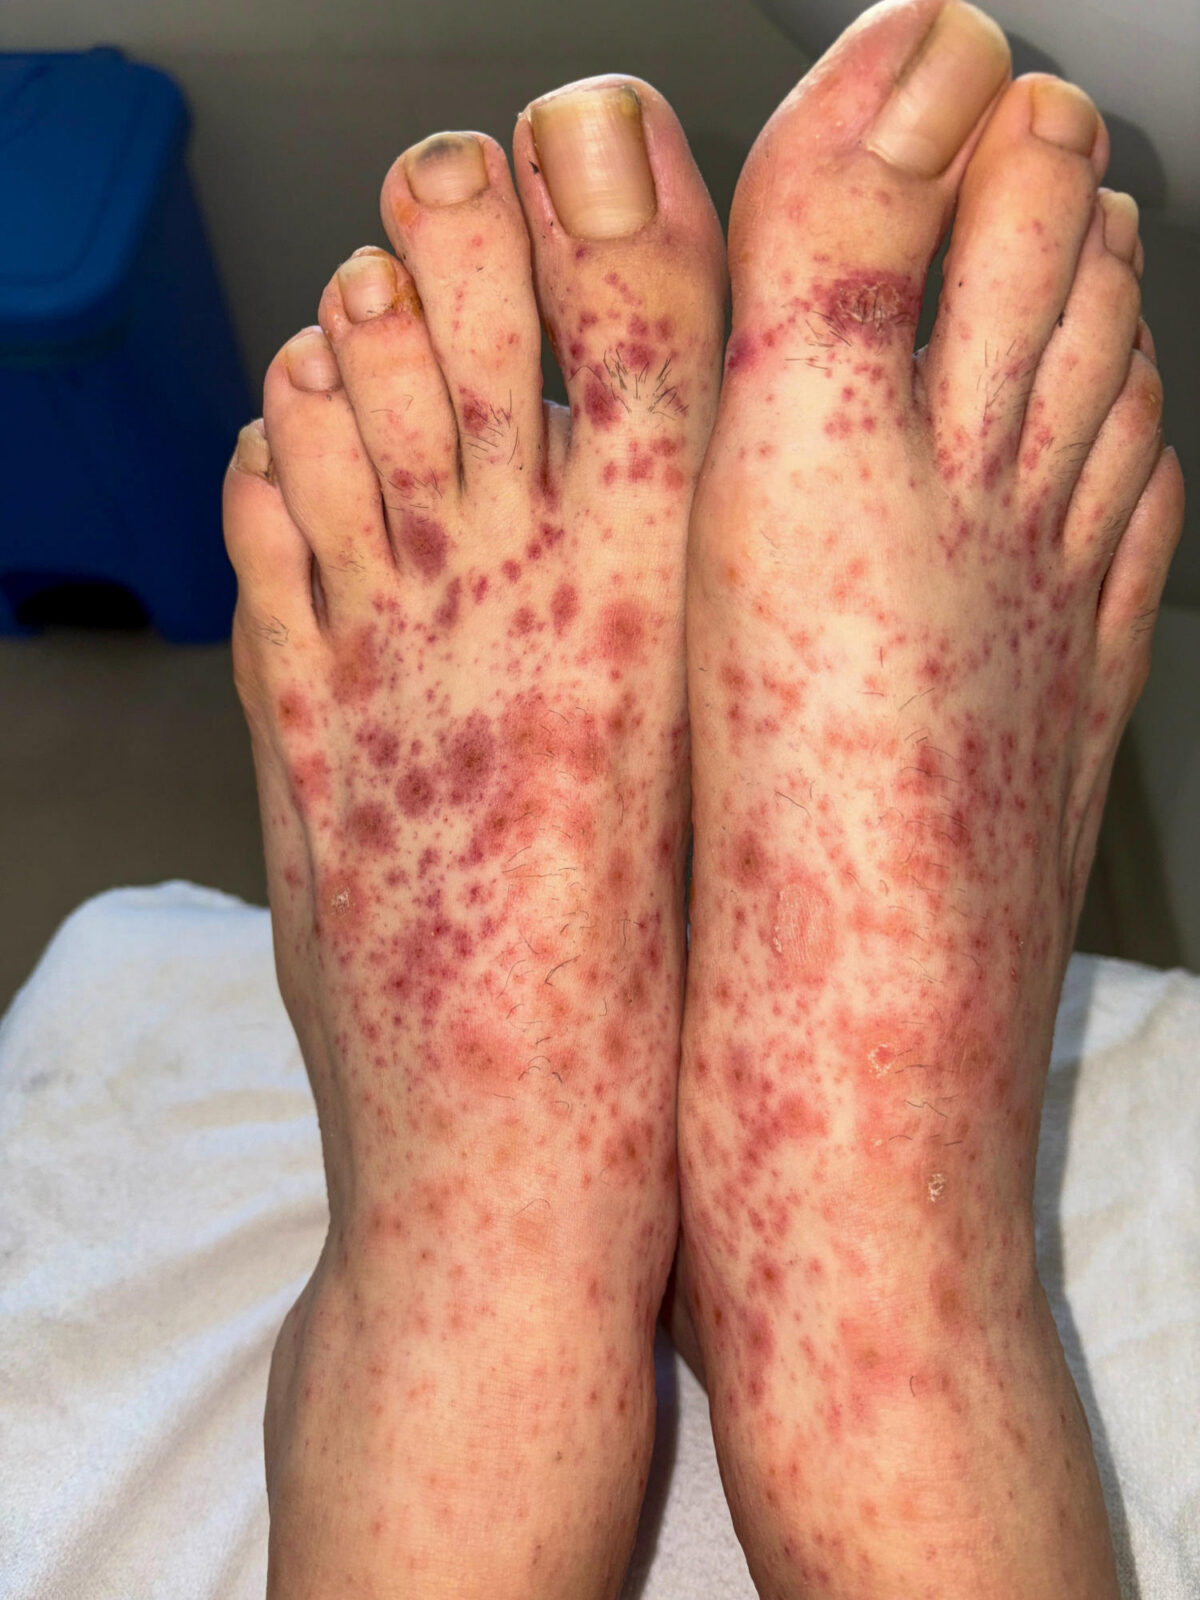
A vasculitis-related rash. Such rashes can appear in some cases of ANCA-associated vasculitis, an umbrella term for a group of rare diseases in which the immune system mistakenly attacks its own blood vessels.
Visual: iStock / Getty Images Plus
Steroids, however, have severe side effects. Within a month and a half of going on the steroids, Cusano recalled, she gained 40 pounds. Her emotions were “just like crazy,” swinging from intense sadness to anger. She had trouble falling asleep, and when she did fall asleep, she was haunted by another side effect: nightmares. “I did not like it at all,” she recalls.
AAV patients may need to take steroids for months to years, and Tavneos was supposed to replace or reduce their use.
David Pisetsky, a rheumatologist and researcher at the Duke University School of Medicine, was on the FDA advisory committee that considered the ChemoCentryx trial data. He voted against recommending approval, in part because many patients in the control group received just one round of a slower-acting medication — rituximab — in addition to steroids when, in the real world, they would have received two, according to Pisetsky. The trial’s design, he said, made the results difficult to interpret.
In an editorial in the journal Rheumatology, Mike Putman, medical director of the Vasculitis Program at the Medical College of Wisconsin, and co-authors would later make a similar case: Patients in the comparison group did not receive treatment consistent with the current standard of care. “It is somewhat debate-able about what the ‘standard of care’ would have been” when the study was done, Putman wrote in an email to Undark. “We had not yet established rituximab as maintenance therapy at that point, though most people were already doing that.”
Other members of the advisory committee were persuaded, including Walter Kraft, a clinical pharmacologist and researcher at Thomas Jefferson University. He voted yes to approval. “I felt the evidence, though limited, met the societal and therapeutic goals,” he said during the meeting. Requiring another trial, he added, could delay the drug’s approval by several years.
But that vote, he told Undark in a recent interview, was “based upon an assumption that the sponsor was following the rules of the road.”
“The entire company can be at stake. That urgency can drive them to work harder and move faster.”
These days, a significant number of drugs approved by the FDA start out at a small company with few or no medications on the market, said Sean Nicholson, an economist at Cornell University. Large companies increasingly recognize that their comparative advantage is not in developing breakthrough science, which is more likely to come from “nimble, small startup biotechs,” so rather than trying to compete, Nicholson said, a big company will look to buy or partner with the smaller company.
That’s what happened with ChemoCentryx, which was bought by Amgen for nearly $4 billion one year after the FDA issued its approval of Tavneos.
When bringing a drug to market, small companies face a slightly different set of incentives from large companies, said David Ridley, a health economist at the Duke University Fuqua School of Business. A large company with many products in its pipeline may more readily abandon an experimental drug rather than invest in costly late-stage testing. “Small companies have more to lose,” he wrote in an email to Undark. “The entire company can be at stake. That urgency can drive them to work harder and move faster.”
“In rare cases,” he added, “they might cut corners.”
Back in May 2021, Tavneos’ approval appeared far from certain. Almost immediately after the FDA released its briefing document for the advisory committee meeting, ChemoCentryx’s stock value plummeted, and its shareholders sued for securities fraud.
Four years later, as part of that lawsuit, a report was filed, alleging that ChemoCentryx had not, in fact, followed the rules of the road. The report indicated that the company’s own trial analysis originally found that the patients receiving Tavneos had not achieved better one-year remission rates than the patients who received the usual treatment.
After company employees unblinded the trial data — meaning they looked to see which study participants had actually received the drug and which had received a placebo — they selected a handful of patients whose remission status would be reassessed. This readjudication, as it is called by the FDA, violated the study’s protocol. What’s more, the agency alleges, the patients were cherrypicked to get the results the company needed for approval.

ChemoCentryx did not disclose the original results, nor the fact that it had reassessed the original data, to the FDA.
In December 2025, Tracy Beth Høeg became acting director of the FDA’s Center for Drug Evaluation and Research, or CDER.
In an email to Undark, Høeg noted that legally, she can’t speak to the specifics of how this issue came to her attention. But, she noted, “One of my key roles as CDER acting director was letting everyone know my door was open, and I encouraged CDER employees to speak openly with me, especially about matters potentially affecting public safety.”
“When I learned of this case,” she continued, “I distinctly remember thinking this story had so much intrigue that it could easily be made into a movie.”
But the repercussions, Høeg argued with unusual candor, are very real. “Essentially ChemoCentryx swindled billions of dollars by developing a drug that gained FDA approval only because they manipulated the data,” she wrote. Since the drug went onto the market, it has been linked to eight deaths and dozens of hospitalizations. “This can be a deadly drug,” wrote Høeg, “and we don’t know if it works.”
Large companies increasingly recognize that their comparative advantage is not in developing breakthrough science, which is more likely to come from “nimble, small startup biotechs.”
Such was the essence of the FDA’s letter sent in April to Amgen, in which the agency proposed to withdraw approval of Tavneos. The retraction of the Tavneos trial data by the New England Journal of Medicine followed two months later, at the request of the study’s two academic authors.
“This will be a pivotal moment for rheumatology,” wrote Putman, in a lengthy essay on Substack. It’s a story not just about Tavneos, he argued, but evidence that the normal systems of scientific oversight — including peer review and regulatory approval — “failed to detect a shocking case” of alleged data manipulation.
According to Amgen, ChemoCentryx’s actions were less than ideal, but they don’t amount to data manipulation — and they certainly don’t warrant withdrawal of Tavneos.
In the 104-page document submitted to the FDA this summer, Amgen said that ChemoCentryx’s re-adjudication doesn’t “align with the approach Amgen would have taken.” Amgen called it “unfortunate” that ChemoCentryx didn’t disclose its actions to the FDA, noting that it, too, had been in the dark about this.
Still, Amgen pointed out, none of the underlying data were actually changed, and the reassessment of the data, Amgen maintains, was “conducted to correct a small number of errors.” ChemoCentryx was not legally required to disclose the fact that it revisited the data to the FDA, Amgen maintains.
Get Our Newsletter

In an emailed response to questions from Undark that Alison Chartan, director of Amgen’s global media relations team, requested be attributed to a company spokesperson, Amgen reiterated many of the points made in the document submitted to the FDA. “As stated in our response to CDER,” the email noted, “the 2019 data readjudication conducted by ChemoCentryx followed a prespecified procedure to correctly and consistently apply prespecified trial rules to adjudicated outcomes. No clinical data were altered.” The email also emphasized the real-world impact a withdrawal would have on those currently taking Tavneos. “Preserving treatment options for these patients,” Amgen wrote, “is central to our mission.” (The company plans to present new data on Tavneos at a conference in November.)
The FDA does have the authority to withdraw its approval of a drug, said Patricia Zettler, a law professor at The Ohio State University who formerly served as an attorney for the Department of Health and Human Services. The law requires a stepwise approach. As an opening gambit, the agency must give notice and offer the drug’s manufacturer an opportunity for a public hearing. If the manufacturer can demonstrate a genuine disagreement about the facts, then the hearing may be held. After that, the FDA can withdraw approval of the drug. If Amgen disagrees with the decision, it could sue the agency.
“When I learned of this case, I distinctly remember thinking this story had so much intrigue that it could easily be made into a movie.”
All of this leaves patients and physicians in a potentially protracted state of uncertainty about whether Tavneos actually works.
Amgen says it does. To make its case, the company has pointed to an independent re-adjudication of its pivotal trial, conducted by researchers at the Duke Clinical Research Institute, part of the Duke University School of Medicine. Although the drug still didn’t meet the FDA’s bar of higher one-year remission rates, the study participants who received the drug fared no worse on this measure. The company also pointed to real-world data, meaning data collected via routine medical care, suggesting that Tavneos can indeed reduce steroid use.
Chloe Cusano is among those who would like to see Tavneos retain its approval. She received it while in the hospital and credits it with helping her taper off steroids more rapidly. Roberts, the UCSF epidemiologist, said his team’s registry study found low rates of drug-induced liver injuries among patients in the U.S., a finding he characterized as “incredibly reassuring,” particularly when care is coupled with careful monitoring. It’s important to keep in mind, he said, that the current alternative to Tavneos is “much higher levels” of steroids.

Others, though, remain skeptical.
Under the law, Tavneos “really shouldn’t remain on the market,” said Joshua Skydel, a clinical fellow in rheumatology at Yale New Haven Hospital and a researcher at the Yale Collaboration for Regulatory Rigor, Integrity, and Transparency. The FDA has standards for drug approval, including substantial evidence of safety and effectiveness. In this case, the pivotal trial has been called into question, and several of the studies that Amgen has pointed to have yet to be published: “I’d at least like to see them go through peer review,” Skydel said, “before hanging my hat on them.”
Høeg, meanwhile, is skeptical that clinical evidence gathered since Tavneos was approved will do much to support its case. “I suspect real world data, much of which were already available when we requested withdrawal in April, will not meet the FDA’s evidentiary bar for approval,” she wrote. “We do know the data were insufficient for ongoing marketing authorization [in] the EU and UK.”
It’s important to keep in mind, epidemiologist Eric Roberts said, that the current alternative to Tavneos is “much higher levels” of steroids.
Skydel additionally noted that at the time of Tavneos’ approval, the FDA requested that additional post-marketing studies be conducted. But Amgen has fallen behind on deadlines for those studies. “This episode really, for me, highlighted the way that drugs are allowed to reach the market with open questions,” Skydel said. “Our capacity to answer those questions is really only as strong as FDA and industry’s collaboration,” he continued, as well as FDA’s willingness to use its authority after a drug has gone on the market.
In its April letter, the FDA argued that the stakes of this debate go beyond patients with one rare disease, stating that withdrawing the drug “is critical to protect the public health and the integrity of the drug approval process.” Absent such a consequence, the agency stated, other companies will have an incentive to act deceptively.
Walter Kraft, who voted to recommend approving the drug based on what he knew at the time, also worries about the potential for knock-on effects. The clinical trial system “is built on a level of trust,” he said. “And when that trust is put into question for a narrow parochial gain, it puts the whole system at risk for other subsequent actors in the space.”