








Interview: The Nerve That Could Transform Medicine


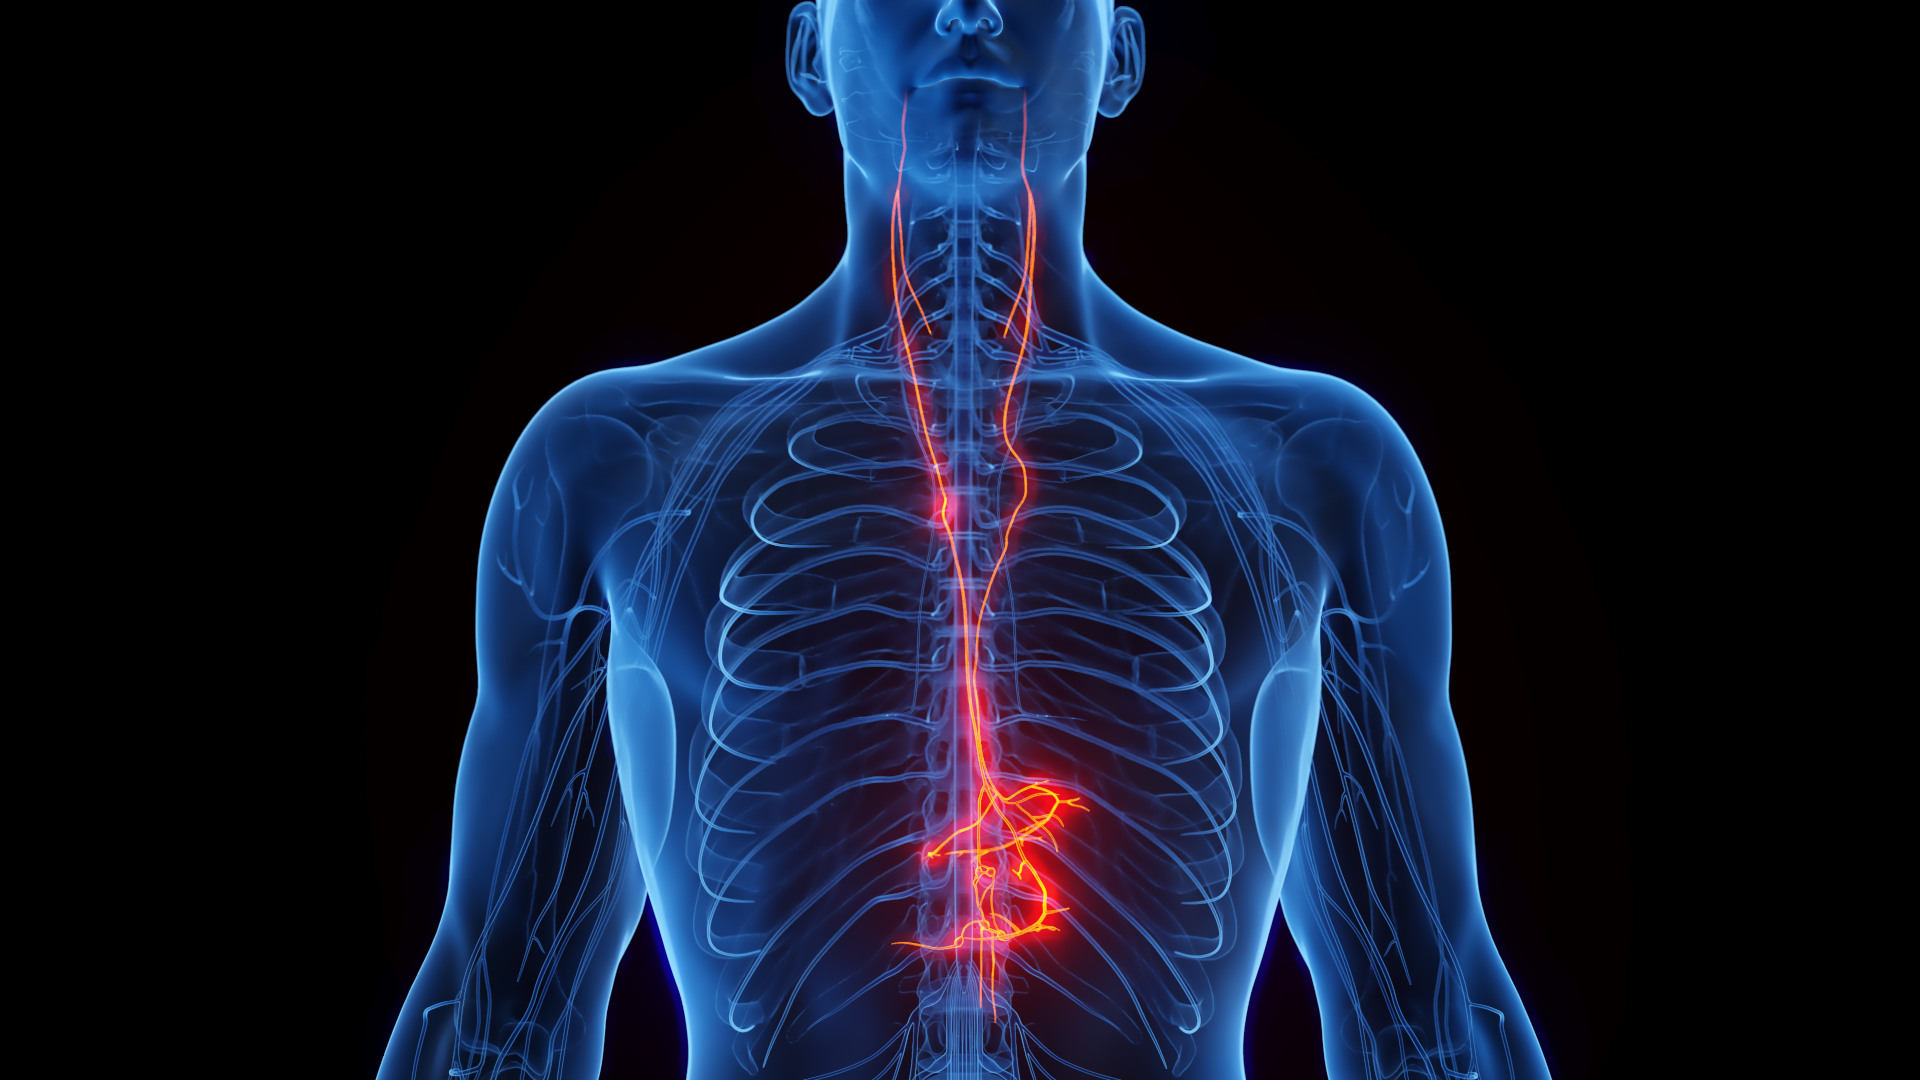
The vagus nerve looks like a long white string that begins in the brainstem and travels down through the neck into the chest, where it branches to organs including the heart and lungs, and down into the abdomen, where it connects with the digestive tract. The nerve communicates through electrical signals that regulate heart rate and breathing, encourage digestion, and generally help the body maintain its normal resting state.
As it turns out, the vagus nerve can also communicate with the immune system, quieting the white blood cells that drive harmful inflammation in conditions like rheumatoid arthritis.

Researcher and neurosurgeon Kevin J. Tracey observes a lab sample of the vagus nerve, which looks like a long white string. Tracey, along with his team, discovered the vagus’s link to the immune system more than two decades ago.
Visual: Feinstein Institutes for Medical Research
It’s “a really beautiful scenario,” said Kevin Tracey, a researcher and neurosurgeon whose team discovered the vagus’ link to the immune system more than two decades ago. Currently, patients with rheumatoid arthritis are prescribed drugs to treat their inflammation, Tracey said in a recent interview with Undark. But these medications don’t work for everyone, and they can cause intolerable side effects while, in some cases, costing the health care system $50,000 to $100,000 a year.
In 2007, Tracey co-founded a company, SetPoint Medical, that developed an electrical device that can be implanted on the vagus nerve in the neck. The idea was that it might offer some patients an alternative to drugs. Last year, the device was approved and this year, a study commissioned by SetPoint found that the device is “highly cost-effective” as a rheumatoid arthritis treatment in the United States.
To date, most of the data behind electrical stimulation as a possible treatment for autoimmune diseases has come from experimental animals, said Matthijs Kox, an expert in inflammation at Radboud University Medical Center in the Netherlands who is not affiliated with SetPoint. The pivotal study supporting approval of SetPoint’s device, he said, has advanced the field by showing the approach is feasible and effective in humans.
Tracey is president of the Feinstein Institutes for Medical Research and is named as an inventor on more than 100 U.S. patents, including some related to the vagus nerve stimulator. He now serves as a consultant to SetPoint Medical and is the author of “The Great Nerve,” a new book that describes the device and the science behind it. This interview took place over Zoom and has been edited for length and clarity.
Undark: What does the implantation of this stimulator entail, and who is a good candidate for it?
Kevin Tracey: Let me tell you who the candidate is first because that’s really important. Under FDA approval or guidelines today, the candidates for this are patients with rheumatoid arthritis who are not having a therapeutic response from the drugs available to them, or [who] are not able to tolerate the side effects of those drugs.
The device is the size of a Tylenol capsule or a fish oil pill. And in that device — in that little, teeny thing — is a battery; the leads, which have the stimulator that goes on the vagus nerve; and an antenna that communicates to a doctor’s iPad. The device is implanted on the vagus nerve. Then a [silicone] pod wraps around the device to hold it in place.
It’s a general anesthesia. It’s come in in the morning and go home in the afternoon. Procedure takes about an hour, give or take, and [the device] is implanted by neurosurgeons. Last I heard, it’s being done now in about 40 or 45 centers in the United States under this FDA approval. Medicare has authorized payment for it, and commercial insurance companies are also beginning to authorize payment for this, which of course is a critical step.
UD: A review of your book in Science was a bit sober. It said the device’s benefits are modest, and in the pivotal human study, just over a third of patients experienced the benefits, and a quarter of the patients in the control group experienced similar improvement. Is this a fair characterization in your view?
KT: There’s a couple of things they left out of that story. Let’s start with the patients because that’s what matters to me. The study design was calling for 250 patients, give or take. They ended up with 242 in dozens of sites. Guess how many patients tried to enroll in the study?
UD: How many?
KT: How many patients went on the portal and tried to apply to be included in an experimental surgery trial of a device they didn’t know worked?
UD: I’m curious — you tell me!
KT: Thirty thousand. From the perspective of a patient who’s out of therapeutic options, what I read into that is: “I want to try this. I want the option.”
So, what happened in that trial? Well, the first thing is the trial hit its primary endpoint [at three months].
A couple of things were really interesting about what happened next. In the drug world, most of the response rates occur in the first three months for rheumatoid arthritis. The drug benefits tend to plateau in almost every case within three months. What happens with the SetPoint system is patients continue to improve for a year. So the benefit was slower in onset, but continued to improve for a year.
The real question is “six months later, in the people who were out of options, what percentage of them would recommend this therapy to their family members and friends? And what percentage of them responded yes?”
Ninety-four percent. It’s a great rate.
Now, was everyone cured? Of course not. No one’s saying that. I’m not saying that. I’m not selling anything here. And neither are my colleagues who’ve done the work on this. But about half of all study participants had a really dramatic response. I’ve met a lot of them, and every time I meet a patient who tells me she can dance at her daughter’s wedding when she couldn’t even button her blouse before the surgery, it brings tears to your eyes. Sometimes she cries, sometimes I cry, sometimes we both cry.
Get Our Newsletter

UD: If someone takes too much of a drug, say Ozempic or Tylenol, they can experience toxicity or bad side effects. Is it possible to overstimulate the vagus nerve, and if so, what happens?
KT: That’s a very interesting comment that requires first a specification on how this works. This device delivers current into the vagus nerve for one minute a day, and the amount of current it delivers is on the order of 400 microamps. Many of the patients have their device programmed to go at 4:30 in the morning, and they sleep right through it. Some patients wake up to a little tingling in their neck for one minute.
We know that that is safe because there is a 30-year experience using a different device, but it’s still a vagus nerve stimulator. That device is used to treat epilepsy or depression under FDA approval.
Those patients will sometimes experience a twitching of their lip or their neck. They will sometimes have a buzzing in their vocal cords when they’re speaking. Some will experience pain. [Editor’s note: Vocal cord issues and pain are also potential side effects of the SetPoint device.]
Most importantly, we know from decades of experience and hundreds of thousands of patients, there’s no evidence of immunosuppression. There’s no black box warning. There’s no evidence of increased risk of lethal sepsis or cancer or tuberculosis — all of which can be found on labels for the drugs that are currently used to treat rheumatoid arthritis.
You can make a very strong case, and I have, that vagus nerve stimulation therapy — we already have evidence — that it’s safer than the current standard drugs to treat rheumatoid arthritis.
UD: I don’t want to take this in a direction that I hadn’t planned, but I am very curious about how this works in the world of regulation. Would this ever become a first line therapy, and what would it take for that?
KT: Dive into this! Now we’re waxing out of the scientific mechanism world into a whole new universe.
Look, I personally have no criticism of what the FDA approach to this has been. They’ve been great. The next step is not regulatory. The next step is payers — payer behavior, paying for this — and physicians adopting a new approach to treating their patients. This is a pioneering idea. This requires rheumatologists collaborating with neurosurgeons.
There are books on this: It requires that the early adopters generate the widespread enthusiasm for the effectiveness and safety of something. It requires patients asking for it, and it requires payers paying for it, and eventually the laggards who are resistant to new — that’s what they’re called, the laggards —
UD: What about “people who just want more evidence”?
KT: Yes, but in the textbooks on adoption of innovation, and there are textbooks on adoption of innovation, you have the early adopters, and you have the laggards. They’re not bad people. They want assurance that this isn’t a flash in the pan. And they want the evidence. Ultimately that comes when the medical societies of the relevant body start to put it on their therapeutic recommendations and guidelines. Until these kinds of new ideas get on the guidelines, you’re going to have the early adopters drive the story.